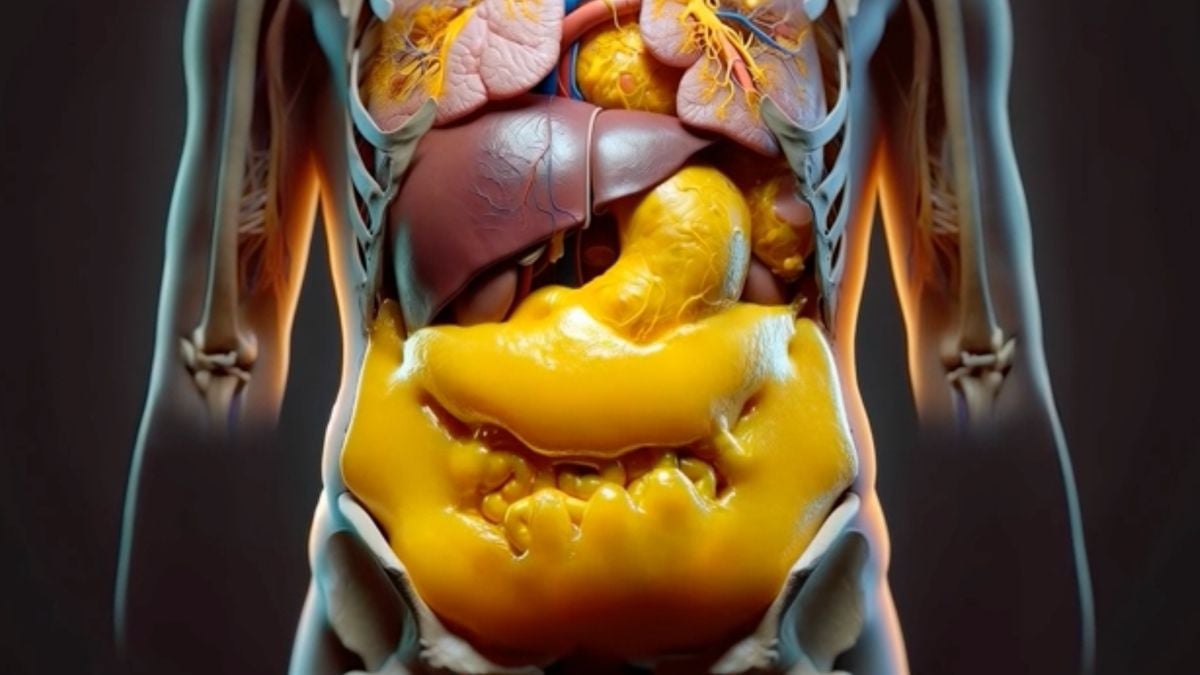
On August 20, 2026, the Journal of the Endocrine Society published "Adiposity, not chronological aging, is the dominant determinant of circulating testosterone in US adult men" by Adam W. Potter and Karl E. Friedl of the US Army Research Institute of Environmental Medicine (DOI 10.1210/jendso/bvag194) — a follow-up to the same authors' July 13 paper, "Low testosterone is a phenotype of visceral adiposity" (DOI 10.1210/jendso/bvag160). ScienceAlert brought the work to a wider audience on September 10, and it lands squarely in the middle of a testosterone-prescribing boom.
Why It Matters
This is a direct challenge to the business model of a fast-growing telehealth category. Afterglow has tracked testosterone prescribing hitting new highs through 2026, the FDA panel push to reconsider TRT's scheduling, the opening of a possible low-libido indication, and a wave of platforms — Hims, LifeMD and others — building recurring-revenue TRT lines. Nearly all of that is predicated on low T as an age-driven deficiency requiring lifelong replacement. If the dominant driver in men under 60 is reversible visceral adiposity, the clinically correct first-line intervention for a large share of patients is metabolic, not hormonal. The competitive irony is sharp. The same telehealth platforms selling TRT subscriptions are, in most cases, also selling GLP-1 weight-loss subscriptions — and this research implies the GLP-1 line may be the better testosterone product for a meaningful subset of the TRT patient panel. Platforms that get ahead of this by screening adiposity phenotype before initiating testosterone will have a defensible clinical story; platforms that don't are exposed if regulators or plaintiffs' lawyers start asking why reversible metabolic contributors weren't evaluated first. That exposure is not theoretical in a year that has already produced FTC action and securities litigation in this category. For the broader male sexual health segment, the practical takeaway is diagnostic rather than therapeutic. Nobody is routinely measuring visceral fat — it requires imaging or a DEXA-style assessment, not a tape measure. If the field accepts adiposity phenotype as the relevant variable, there is a genuine gap for accessible visceral-fat measurement in men's telehealth workflows. That is a device and diagnostics opportunity sitting in plain sight.The finding is straightforward and awkward for the TRT industry. Reviewing health data from nearly 5,000 US men aged 20 to 59, the authors report that visceral adipose tissue — the deep abdominal fat that wraps the liver, stomach and intestines — was strongly associated with testosterone suppression, and influenced testosterone concentrations significantly more than chronological age did within that age range. After accounting for fat distribution, age showed only modest associations. Their conclusion is that deep belly fat should be treated as the "primary adiposity correlate of low testosterone in US men."
That reframing has teeth because the conventional story is so entrenched: testosterone declines gradually from about age 35, therefore low T is an aging problem, therefore the fix is replacement. Friedl and Potter's data suggests age is doing far less work than assumed. The mechanism is plausible on established biology — visceral fat is dense in testosterone receptors, promotes insulin resistance that may impair how Leydig cells convert cholesterol to testosterone, and drives inflammatory signaling that can increase conversion of testosterone to estradiol. Their work also aligns with earlier literature: a 2007 study of 1,667 men found that gaining 4–5 BMI points was associated with a testosterone decline comparable to roughly ten years of aging, and a 2013 study tracking 1,382 men over five years concluded age-related declines are "not inevitable" but largely explained by smoking, obesity and depression.
The authors are pointed about the clinical implication: "These observations underscore the importance of characterizing the underlying adiposity phenotype and considering reversible metabolic contributors before initiating testosterone therapy." ScienceAlert notes the corollary that interventions reducing visceral fat — including GLP-1 receptor agonists such as semaglutide and tirzepatide — may address low testosterone more directly than replacement alone. A secondary caveat in the work is that BMI and waist circumference, the two measures most clinics actually use, are poor proxies for visceral fat: men with identical BMIs can carry very different visceral loads, meaning a lean-looking young man may be at risk while a muscular older man is flagged purely on age and BMI.
Sources
- Visceral Fat, Not Aging, May Be The Real Driver of Low Testosterone — ScienceAlert
- Adiposity, not chronological aging, is the dominant determinant of circulating testosterone in US adult men — Journal of the Endocrine Society (Europe PMC)
- Low testosterone is a phenotype of visceral adiposity — Journal of the Endocrine Society (Europe PMC)
Update — 2026-09-12
Initial entry — story first created.